The sequel
Can one pandemic make the next more likely?
Yes, if its effects last. A pandemic can leave fewer rangers in parks, fewer vaccinated people and pathogens better adapted to humans. An animal outbreak can leave a farm primed for the next one. Antibiotic resistance can make a later outbreak deadlier without making it likelier. Most of these couplings come from separate settings, and nobody has yet followed one pandemic through to the next.
During covid, travel restrictions cut visitor income at some national parks. IPBES describes rangers and guides laid off and enforcement against illegal extraction weakened, with poaching up in one place and anecdotally up in another.
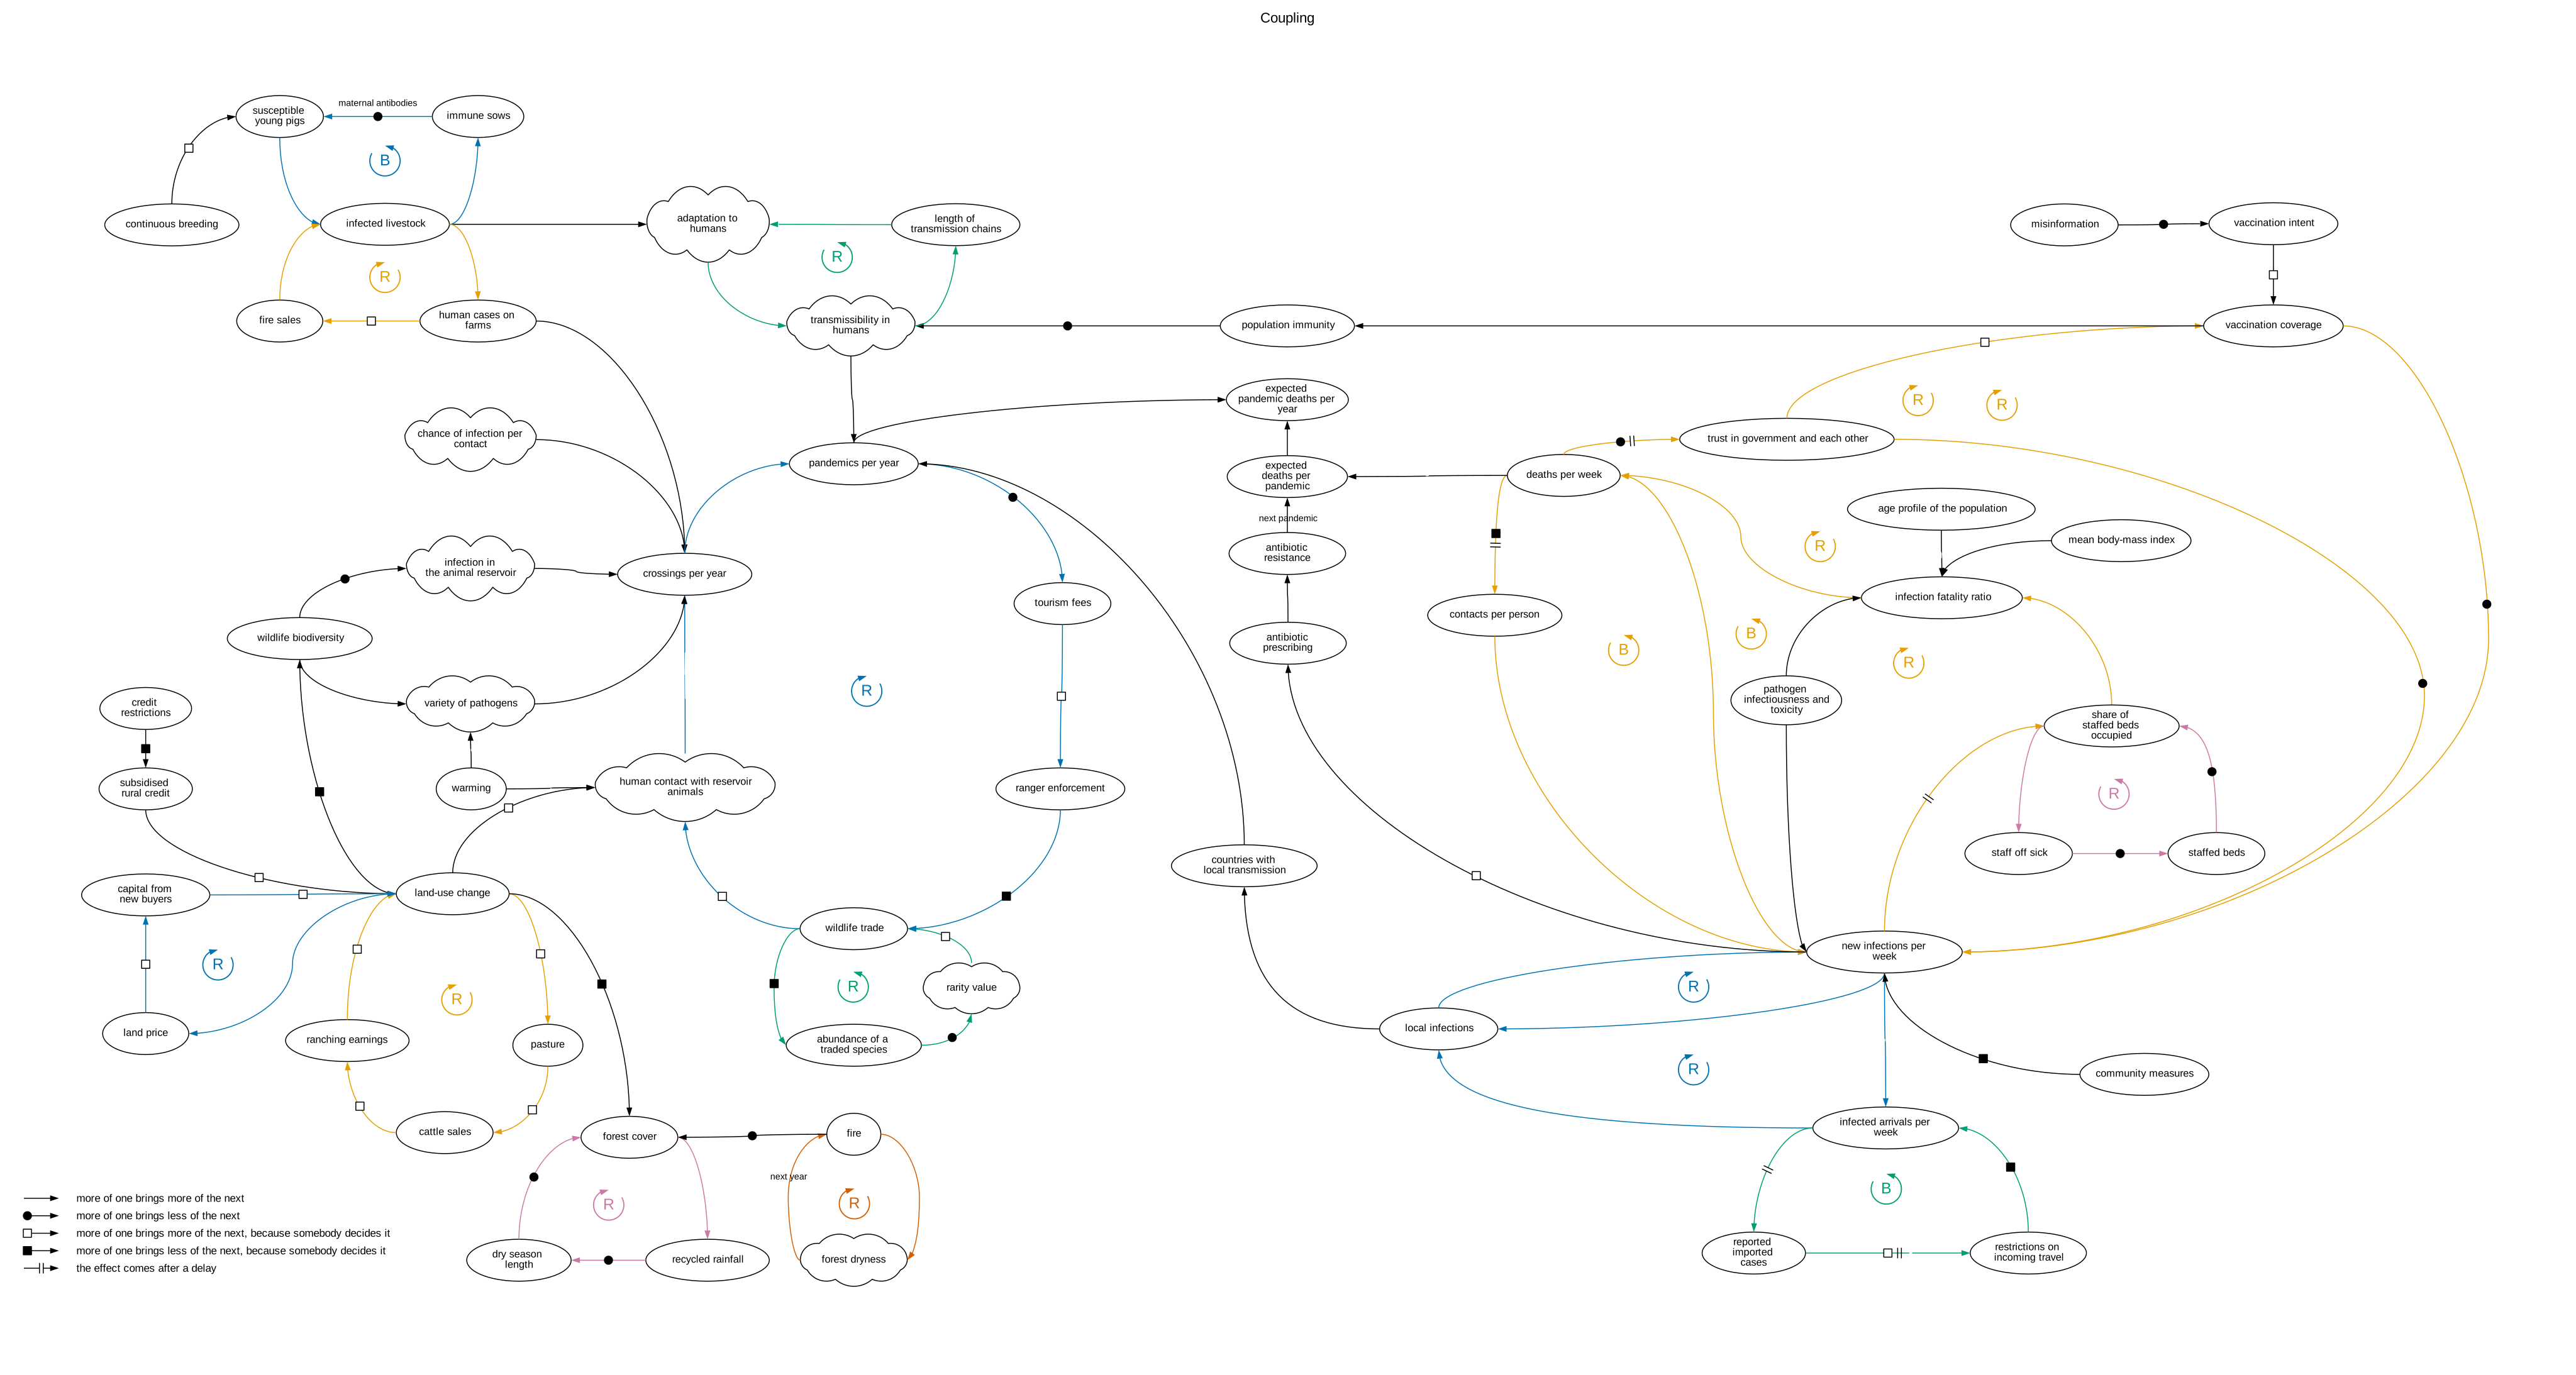
Click to enlarge. The proposed park loop carries risk between outbreaks; the faster loops may change the course of a wave already under way. R reinforces, B balances.
The rangers go home
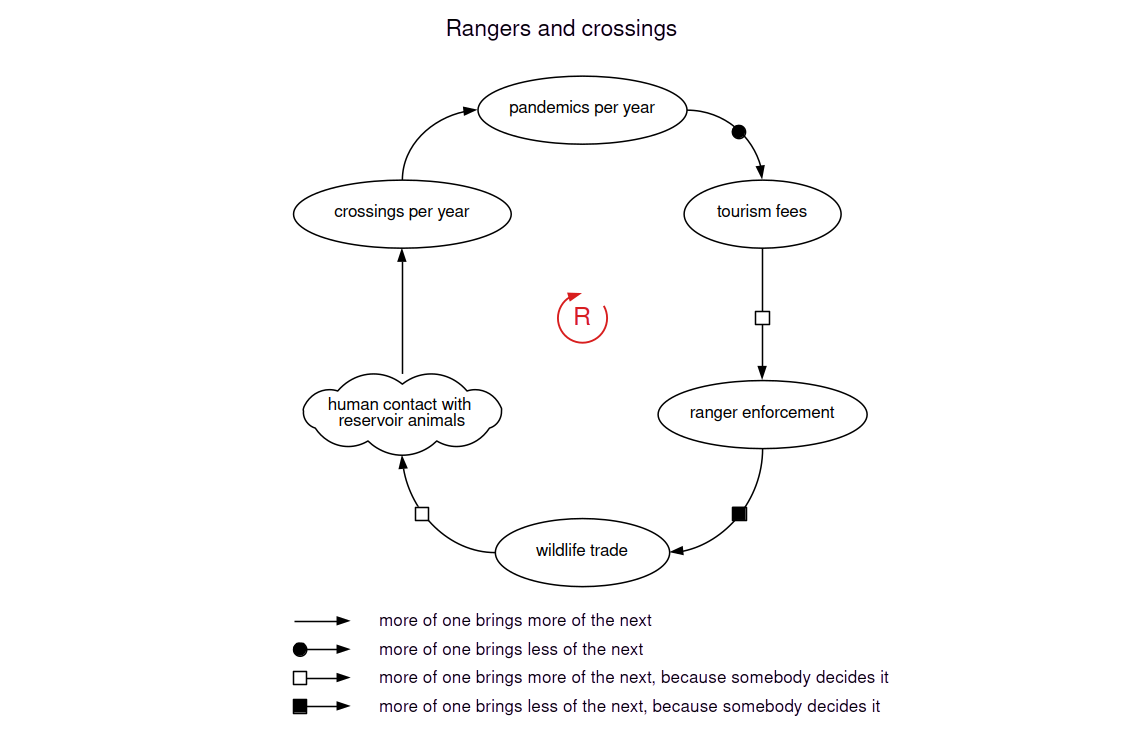
The unmeasured step is whether weaker enforcement changes how often people meet animals carrying pathogens.
A review of seventy studies found that logging and poaching rose after health shocks more often than they fell. The studies cover different shocks, mostly as qualitative accounts or single cases. They give the direction of the pressure.
Visitor income may return, or public money may replace it. Nobody has recorded how long park budgets stayed low. If protection recovered quickly, this route would not carry into a later outbreak.
Beds run short
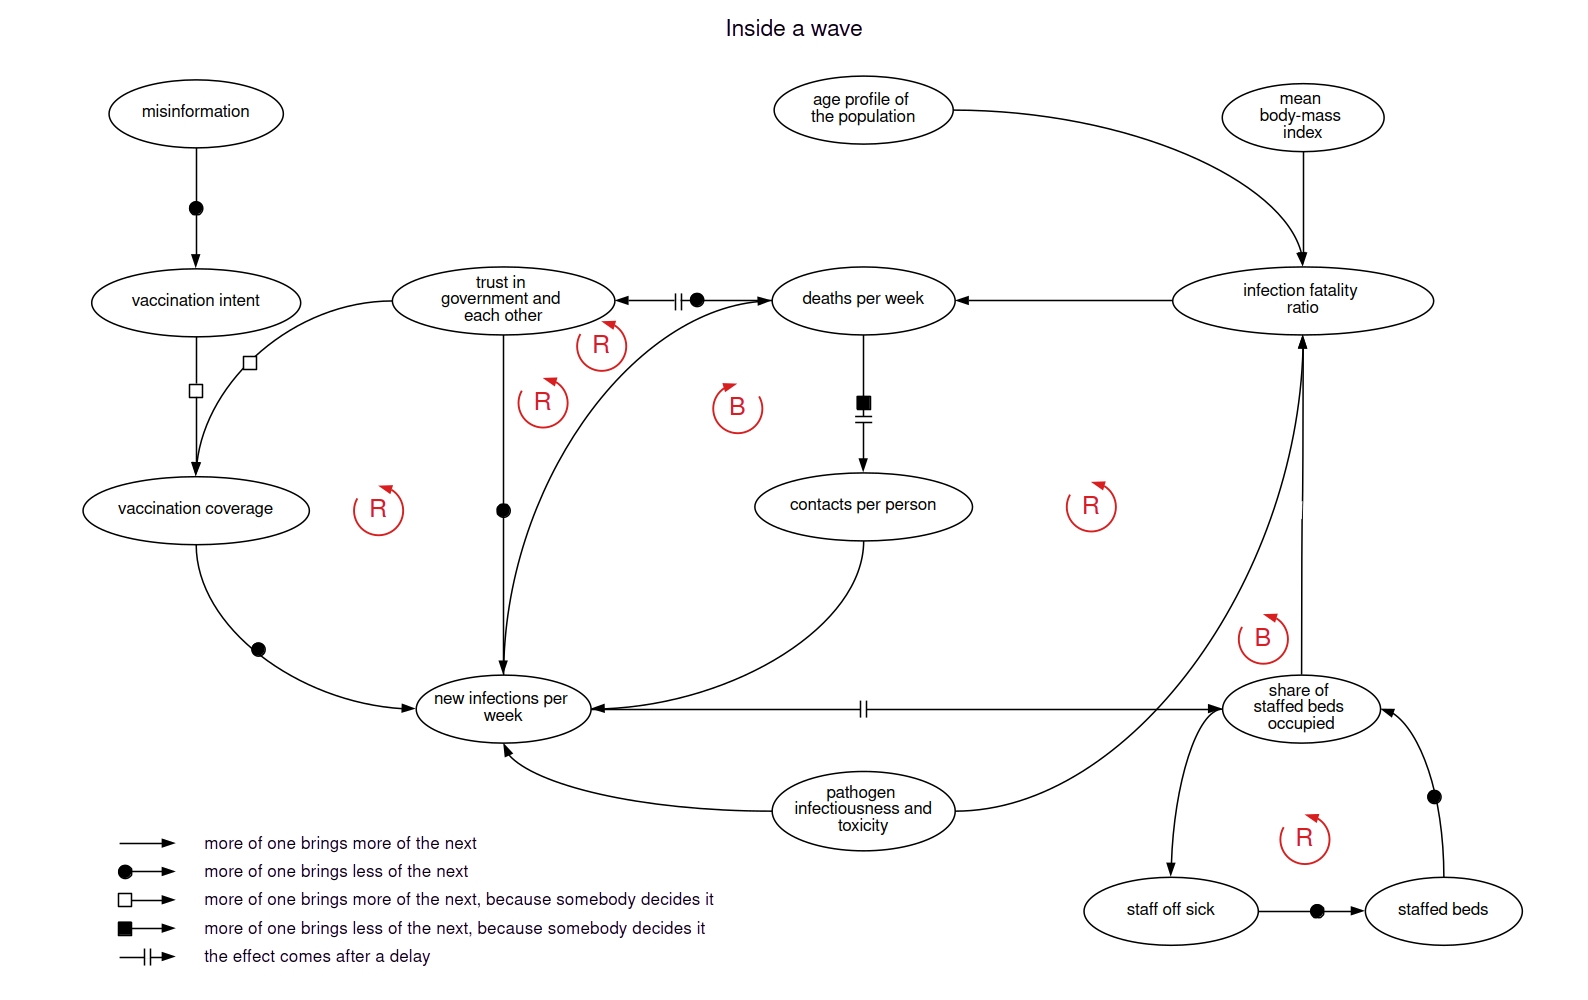
The weekly loops can push hospitals harder, or slow spread once people cut contacts.
The seven loops
Reinforcing (R):
more new infections per week → more deaths per week → less trust in government and each other, after a delay → more new infections per week
more new infections per week → more deaths per week → less trust in government and each other, after a delay → lower vaccination coverage → more new infections per week
more new infections per week → higher share of staffed beds occupied, after a delay → higher infection fatality ratio → more deaths per week → less trust in government and each other, after a delay → more new infections per week
more new infections per week → higher share of staffed beds occupied, after a delay → higher infection fatality ratio → more deaths per week → less trust in government and each other, after a delay → lower vaccination coverage → more new infections per week
higher share of staffed beds occupied → more staff off sick → fewer staffed beds → higher share of staffed beds occupied
Balancing (B):
more new infections per week → more deaths per week → fewer contacts per person, after a delay → fewer new infections per week
more new infections per week → higher share of staffed beds occupied, after a delay → higher infection fatality ratio → more deaths per week → fewer contacts per person, after a delay → fewer new infections per week
Most of the hospital path remains a chain of plausible mechanisms rather than a tested causal sequence. One relationship has been measured: higher intensive-care occupancy was associated with higher mortality. What produced that association, including any contribution from staff shortages, remains uncertain. The measured links run from new infections and the infection fatality ratio, the share of infected people who die, to deaths per week. Bollyky and colleagues found that countries with more trust had fewer infections. If that association were causal, Denmark’s level of interpersonal trust everywhere would have meant about 40% fewer infections. The loop back, from deaths to lost trust to lower vaccination and more infections, is a jump.
People may cut contacts after deaths rise; border restrictions start after cases are reported. In Chinazzi’s model of China, a 90% cut in travel to and from mainland China changed the epidemic little unless community transmission also fell by at least half.
After the wave
A pandemic carries risk forward only through what stays changed after the wave. No source shows that more frequent pandemics make any one wave spread faster.
Park income and enforcement could affect future spillover risk if they stay low long enough to change contact with wildlife.
Population immunity decides whether a pathogen already circulating among people can sustain itself. Monkeypox transmissibility appears to rise as the share of people with smallpox-vaccine immunity falls (human transmission).
Trust and vaccination could carry risk forward too. A pandemic that left either low would hand a later pathogen more susceptible people.
Longer chains of human infection give a pathogen more chances to adapt to people. Adaptation that raises transmissibility would help an infection sustain itself, an intuitive jump (human transmission).
In the Nipah farm outbreaks, one animal outbreak set up the next. After the first wave, immune sows passed temporary antibodies to piglets. As new piglets lost that protection, susceptible animals returned, and a likely reintroduction led to persistent circulation. Later, farmers sold pigs after human cases, and infected pigs carried the virus to other farms.
Antibiotic resistance can worsen a later outbreak without making it more likely to begin. Resistant bacteria selected during one outbreak may persist. When a later outbreak brings bacterial pneumonia, resistance to the needed drugs could raise deaths (resistance and pneumonia).
A few levers
Replacing visitor fees with public funding could keep rangers employed when tourism falls. Whether that keeps enforcement up and crossings down is untested.
The clearest measured effect acts on the clearing itself. After Brazil’s 2008 rural-credit rule, Amazon deforestation ran about 60% below its estimated counterfactual from 2009 to 2011. The study did not measure crossings.
Other levers act once a pathogen is spreading. EFSA ranked cattle-movement bans among the most effective measures for limiting spread from one infected dairy farm to another in the EU. In a randomised trial, misinformation cut stated vaccine intent; actual uptake was not measured.
Sleeping in the dungeon
Lord Vetinari: “Never build a dungeon you wouldn’t be happy to spend the night in yourself.”